Recommendations 46st PBF Mombasa course

Class 46

Class 46

The 46th PBF course ended the 1st of May 2015 in Mombasa.

There were 32 participants from Nigeria (11x), Kenya (8x),  Zimbabwe (6x), Malawi (5x), Rwanda (1x) and Kyrgyzstan (1x). All participants passed the final exam and there were six distinctions of 90% or more.

The next English Mombasa course will be organised from July 27th to August 7th (contact Godelieve van Heteren at sina_health@hotmail.com or robert_soeters@hotmail.com The next open French spoken PBF will be in Cotonou from October 12nd to 23rd –  contact Aoudi Ibouraima at aaoudi1@yahoo.fr

RECOMMENDATIONS OF THE PARTICIPANTS

1. NIGERIA

PBF started in 2011 in Ondo, Nasarawa and Adamawa States in Nigeria with a loan program of the World Bank and administrative support of the National PHC DA and State PHCDA. The program was scaled up to 50% of the Local Government Authorities in the three states. The PBF program considerably improved output and quality of the services and there is great enthusiasm. Yet, there are also a number of challenges, which can be tackled when there is enough technical staff trained in PBF to create a sufficient critical mass of PBF champions.

Nigeria federal level team recommendations

  • Develop an Action Plan for the Implementation of PBF in all States in Nigeria;
  • Sensitize stakeholders at the State level and create platforms for interaction between PBF implementing states and non-implementing States using the PBF alumni
  • NPHCDA should use the national health fund to create a budget line for PBF implementation in all the States
  • Conduct advocacy by visiting relevant stakeholders and present PBF at the Federal MOH TMC meeting and the different Technical Working Groups of the National Health Act – 2014 Implementation Committees to obtain their collaboration.
  • Conduct PBF presentations and Memo’s to the National Council on Health. Upon adoption of PBF by the National Council on Health, States will be encouraged to roll out business plans on how to roll out PBF.
  • Create legal backing for the implementation of PBF in line with existing structures in order to avoid duplication of activities, wastages and conflicts at all levels.
  • The team will also work further to ensure the development and operationalization of the National PBF Policy in Nigeria.

 Nigeria State level recommendations

  • The implementation of PBF in the three states should be according to the PBF best practices;
  • PBF should be scaled up to the remaining 50% LGAs in the 3 states and the DFF approach should be abolished, which was only meant as an impact study technique;
  • The key actors implementing PBF should be remunerated (regulators, CDV agency etc)
  • More policy makers should be trained as change agents in order to create a critical mass of PBF champions in Nigeria.

2. KENYA

Mombasa sunrise

Mombasa sunrise

Kenya is engaged in an administrative devolution process of services towards a system with 47 autonomous Counties. This devolution process is still young and also directly affects the health services. Lessons learned and mistakes committed are gradually becoming available.

There are the following issues and challenges:

  • The Public Finance Management Act of 2012 states that all funds should pass through the County treasury. Yet, this limits the autonomy of PBF health facilities.
  • There still seems to lack the political will and leadership to directly invest in health services. Decision makers require more knowledge about PBF.
  • Skilled health personnel are insufficient in particular in peripheral health facilities. Kenya may not have a total shortage of skilled health workers but moreover a distribution problem of lacking incentives to work in remote counties and health facilities. PBF may solve this problem;
  • Insecurity is rife in some Counties. Emergency PBF approaches may be proposed to assist the distressed populations
  • Poor infrastructure in terms of building, roads, equipment etc. Standard PBF approaches with investment units may assist health facilities to improve their infrastructure and buy equipment
  • Poor participatory planning and budgeting
  • If the facility management team can plan for user fees and is given the authority to use the revenues, this will lead to improved quality services and improved motivation;
  • PBF may be applied in public, private and FBO facilities, thus creating a more competitive environment and choice for patients;
  • PBF provide incentives to health workers that perform better in the health sector and thus contribute to better health outputs;

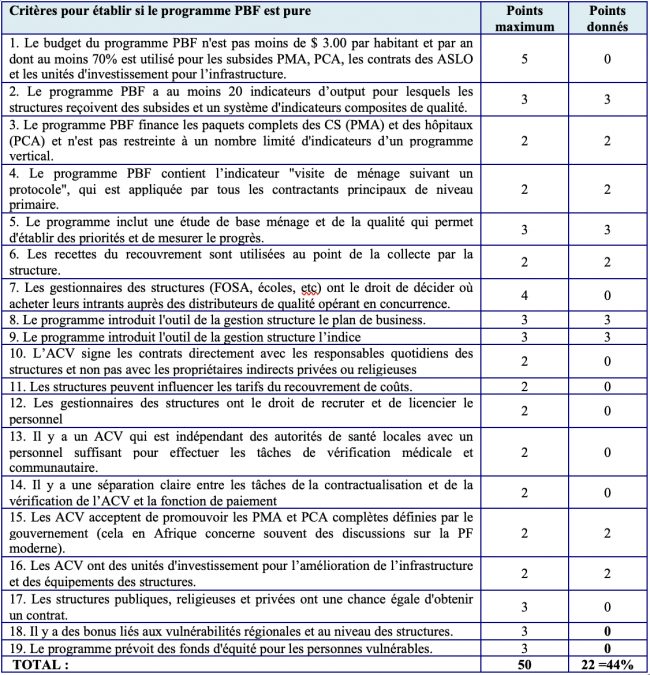
The feasibility based on 19 PBF criteria showed a score of 50%. The main recommendations are the following:

Kenya recommendations

  • Increase the subsidies given directly to the health facilities, which is currently far below the 70% of the national budget that PBF proposes to pay in cash performance payments directly to health facilities and community programs.
  • Increase the number of RBF indicators at basic health package level from the current ten towards at least twenty.
  • Facility managers should be allowed to buy their inputs from accredited distributers instead of receiving drugs from the central medical stores (KEMSA).
  • Create in each County a separate CDV agency for the contracting process, verification and coaching. Currently a joint verification committee, connected to the county medical teams, does the verification. There is not really a separation of functions.

The Kenyan team proposed the following advocacy strategies:

  • Sensitizing the county health management teams on the PBF concepts
  • Sensitizing the county executive committee members for health & the chief officer for health on the PBF concepts and PBF’s benefits
  • Sensitizing and advocating for PBF with the county assembly committee for health
  • Pilot PBF in at least two health centres and three dispensaries in each County

3. MALAWI

In the recent past, the Malawi public services had as one of its main paradigms to provide free health services and primary education. Many people, however, now realize that what is wanted is not just providing ‘services’ but ‘quality services’.

Malawi has been implementing decentralisation reforms since the early 1990s and government is currently devolving various functions to 35 local government authorities. Providing quality services cannot merely be resolved by increasing government expenditures. It must be matched with at the same time improving the design, implementation and monitoring of the system. Moreover, there is a need to change people’s mind-set and make citizens aware that they also take the responsibility of their own destiny and reflect what they ought to do for themselves and their country. Performance based financing is an approach that supports social entrepreneurship instead of only being ideologically driven by unrealistic advocates of social justice. PBF aims at wide reforms and is, in fact, a new reform approach.

Malawi recommendations

  • Reorienting public service delivery from merely increasing access to also improving quality;
  • Providing performance incentives to public servants and thereby to improve service delivery;
  • Enhancing the collaboration among staff from various sectors
  • Enhancing the drive towards decentralization through advocacy for autonomy for public service providers at the local levels;
  • Motivating facilities (school, health, etc) to produce more and better quality services and thus receive performance bonuses. This extra income should also be used to improve working conditions and staff salaries
  • Separating functions to enhance good governance. It is a ‘purchaser – provider split’ e. a split between purchaser (at district level), regulator (ministry), inspection, provider (schools or hospitals), beneficiaries (communities).
  • Target remote facilities providing services with extra payments for the same activity.
  • Train and contract community groups to conduct satisfaction surveys (school or health). The results should be discussed with school managers and teachers, health staff or other service managers, so that they obtain feedback on their performance.

4. ZIMBABWE

Mombasa village

Mombasa village

During a couple of years Zimbabwe experienced severe socio-economic decline that weakened the social services. In 2010, the Ministry of Health received funding support from the World Bank to finance the health services through results based financing mechanism in 18 rural districts. The project supported primary health facilities and referral hospitals. Based on the encouraging results, the MOHCC and the partners decided in January 2014 to roll out RBF to the remaining 42 rural districts. The urban areas are not yet included in PBF but hopefully they will also start applying urban PBF similar to experiences such as in Cameroon.

The Zimbabwe delegation in Mombasa conducted a PBF feasibility scan which produced a 66% score indicating that there are still steps to be made towards a more pure system.

Zimbabwe recommendations

  • Expand scope of programs incorporated in PBF: TB, HIV, Malaria, NCDs
  • Expanding scope may increase indicators, and funds available for PBF per capita per year
  • Adapt a standard protocol, train personnel, and pay VHWs according to performance
  • Cost recovery mechanisms to be adopted for sustainability
  • Involve private facilities in the PBF contracts that may help government to improve quality care, reduce costs and improve HMIS reporting of all activities instead of only for government facilities.
  • Formalize some cost recovery measures whilst giving the local facility and health centre committee the task of identifying vulnerable clients for exemptions.

5. KYRKIS REPUBLIC 

a.NuristhanHealth reforms in Kyrgyzstan has achieved almost universal access to health care and increased efficiency by reducing excess hospital capacity and reallocating funds to primary health care facilities. However, the quality of care remains a problem. The WB RBF project focuses on district-level hospitals with the aim of increasing provider autonomy and accountability and improving structural aspects and clinical processes of care.

There are the following challenges that may need t be addressed:

  • The project does not pay for output indicators, but focuses exclusively on quality measured using a balanced scorecard containing about 150 indicators.




45th PBF course in Cotonou April 2015 with participants from Benin, Niger, Cameroun, BF and Ivory Coast

Participants group 45

The 22 participants and the facilitation team of the 45th PBF course

The 45th PBF course in Cotonou took place from 23 March to 3 April 2015, with 22 participants from Niger (10), Benin (5), Cameroon (3), Burkina Faso (3), and Ivory Coast (1).

The participants appreciated the course, with an average score of 85% on the daily evaluations, compared to 79% for the 22 previous French courses. Satisfaction with the facilitation was 93%. 

Here is the course report (rapport).

CONCLUSIONS for EACH of the PARTICIPATING COUNTRIES

Beach Cotonou

Beach Cotonou

Niger will start PBF in the health district of Boboye in the Dosso region, with technical support from the World Bank, covering a population of 400,000.

Participants’ recommendations for Niger:

  1. Authorities should apply all PBF best practices in the pilot project;
  2. The course group will inform and create awareness about PBF among the administrative authorities, local elected officials, partners, etc ;
  3. The project should establish a Regional Contract Development and Contracting Agency instead of a central one;
  4. The project should conduct the mapping of public and private health facilities in the pilot area and sign contracts (primary and secondary) both with public and private health facilities;
  5. Define the indicators for the community PBF activities.

Benin

The country has achieved good results since 2012 with the RBF program, notably: (1) improved health worker motivation; (2) improved professional quality; and (3) ownership of the peer assessment approach by district hospital staff.

Yet, the program still has a low RBF feasibility score of 44%.

The Benin team conducted an analysis of the RBF program’s feasibility score in the country, revealing the following issues:

  • A budget of less than USD 4 per person per year ;
  • Limited autonomy for health facilities due to centralized human resources management, restrictions on sourcing supplies from multiple distributors, and a lack of authority to set cost-recovery rates ;
  • Exclusion of private health facilities from eligibility for a primary RBF contract ;
  • Absence of geographic equity bonuses for vulnerable regions, districts, and health facilities ;
  • Lack of equity indicators that allow reimbursement of care for vulnerable individuals, thereby exempting them from direct cost-recovery fees.

Strategies to strengthen the health system and the RBF in Benin:

  • Integrate other MOH departments in the consultation about the PBF;
  • Obtain the government’s commitment to maintain an appropriate level of governance to ensure the success of the RBF, including progress towards decentralization;
  • Provide more autonomy to health facilities to purchase essential drugs, equipment and recruit staff;
  • Ensure that the innovative initiatives (community RBF, quality improvement bonuses, involvement of the private health sector, …) are not diverted into vertical programs, but retain their cross-cutting nature;
  • UNICEF, through its mission to the realization of the rights of children in accordance with the Convention on the Rights of the Child (CRC), is part of this process in Benin not only to strengthen the acquired high-impact package at community level but also at health facility level to fight against child, maternal, and neonatal mortality.

Burkina Faso started a PBF pre-pilot in 2010 in three health districts. The pilot was extended in 2014 to 15 health districts, covering 4.2 million people (25% of the BF population). The results are satisfactory, but the feasibility scan score of 68% could still be improved.

Participants’ recommendations for Burkina Faso:

To the Ministry of Health: (1) Continue the expansion of PBF to all districts in the country; (2) Ensure the sustainability of the PBF strategy; (3) Ensure proper implementation of all PBF best practices.

To the partners: (1) Provide more funding for PBF; (2) Assist Burkina Faso towards the upscaling of PBF to all districts.

The Cameroon – Far North Region. 

The Cordaid-funded PBF pilot started in January 2012 and has produced satisfactory results. The local Contract Development and Verification Agencies is the Association for the Promotion of Health in the Far North (APROSEN). The feasibility scan score is 66%.

Participants’ recommendations for Cameroon:

  1. Traditionel hut in Ouida

    Traditionel hut in Ouida

    Integrate the health facilities currently covered by Cordaid and APROSEN in the PAISS / World Bank PBF program;

  2. Develop emergency PBF indicators to respond to the insecurity in the Far North caused by the Boko Haram insurgency;
  3. Review and improve the PBF equity indicators to assist the vulnerable;
  4. Take into account that the local CDV Agency (APROSEN) already has good knowledge of the region.

Ivory Coast. The government and the World Bank plan to implement a PBF program for around 3.5 million inhabitants. Few private organizations in the Ivory Coast are yet involved in the various PBF functions. To address this gap, the Global Challenge Corporation offers technical assistance.

The March 2015 Douala PBF course

Participants at national monument in BueaThe 44th PBF course finished the 13th of March 2015 in Douala.

There were 47 participants of which 14 from the Central African Republic and 33 from Cameroon. All participants passed the final test and there were 9 distinctions which implies a score of 90% or more. There were nine education sector participants from the Central African Republic.

The main recommendations of the course participants were the following:

  • There is an urgent need to strengthen the PBF Unit in the Ministry of Health in Yaounde. They require to cement PBF in Cameroon by coordinating the different RBF programs such as PBF, voucher, value for results. The Unit should equally defend the PBF best practices and transform input budget lines into performance based financing budget lines. They should also monitor and verify the achievements and the performance payments of the regional CDV agencies.
  • Assure the installation of robust contract development and verification (CDV) agencies. This requires setting clear terms of reference for a well-remunarated CDV staff with the autonomy to implement their tasks and without interferon from different input strategies;
  • Visit to Limbe

    Limbe beach

    Revisit the community PBF indicators and assure that only qualified health workers conduct curative patient care;

  • Start the HGOPY tertiary hospital PBF program in all its departments;
  • Conduct research on how to integrate the voucher system in the overall PBF health package indicators and thereby to reduce the administrative costs of the classical voucher system;
  • Start as soon as possible the World Bank supported PBF program in 4 regions of the Central African Republic and change the current emergency general free health care policy into a targeted free health care for the vulnerable.
  • Further strengthen the education PBF program in Central African Republic which considerably increase the money injections in the schools to assure quality and change the different input financing modalities of partners into results based performance payments.

The Sierra Leone PBF course

Freetown Beach

The Freetown Beach is quiet due to Ebola

The 43rd PBF course finished in Sierra Leone at the 31st of January 2015. The course for 28 participants came exactly at the right moment when Sierra Leone also started reviewing its post-Ebola recovery program.

The current PBF “light” approach in Sierra Leone has achieved encouraging results. Yet, there are design problems and challenges such as the weak capacity to contract, verify and coach the health facilities and the unclear separation of functions in particular between regulation and contracting.

In line with the TOR the course participants conducted a review and feasibility scan of the current PBF system and proposed improvements for the next PBF PLUS phase.

Recommendations:

28 participants PBF course Sierra Leone

The 28 participants of the January PBF course in Sierra Leone

  1. Strengthen the existing PBF system by applying best practices and instruments.
  2. Increase the current annual budget of USD 3.2 million to USD 24 million per year. This would increase the current per capita PBF spending from USD 0.50 to USD 4.00 per capita (best practice) and hence also account for certain elements of the Free Health Care Initiative. This is not necessarily fresh finding but might also include the reallocation of existing input budget lines such as for essential drugs, equipment and infrastructure.
  3. Contribute to health system strengthening in the post-Ebola recovery strategy.
  4. Increase the quality of care through a whole set of quality improvement measures including performance incentives for the various functions in the health system.
  5. To allow for efficient use (more value for money) and better coordination of available funds such as from the government, partners and private out-of-pocket expenditures.
  6. Encourage good governance and increase the accountability through the separation of functions and improved verification & auditing mechanisms.
  7. To strengthen public-private-partnerships at the providers level, organising CDV agencies and selecting local NGOs for community verification.
  8. To strengthen the regulatory role of the Government of Sierra Leone through its MDAs and clearly defined relationships with the stakeholders (providers, community voice, verification agencies, payment agencies, partner organizations and civil society organisations).
What do you see?

We do not always see the same fact in the same manner?

Once the above recommendations are applied, international comparative experiences shows that the quality, efficiency and equity of the health services would greatly improve, and the system’s resilience in times of crisis hugely enhanced. It would restore the confidence of the population in the health system. Sierra Leone has the potential to become one of the PBF frontrunner countries in English-speaking Africa.


The December 2014 PBF course

Participants 42nd PBF course

Participants 42nd PBF course

The 42nd PBF course ended in Mombasa at 12 December 2014 and hereby the report.

There were 25 participants. 14 from Nigeria, 3 from Uganda, 2 from Lesotho and Burundi and 1 from Malawi, Mozambique, Cameroon and Zambia.

21 participants were from the health sector but there was also 1 participant from the Local Government in Uganda, 1 from Civil Service Reform Commission in Malawi, 1 from the education sector in Burundi and 1 participant from the Cordaid loan section in Burundi.

The PBF journey is not always smooth

The PBF journey is not always smooth

Studies published in November 2014  showed that PBF worked in Burundi. Yet, at the same time the studies also provide warnings that if the underlying best practices in PBF are not maintained that there will be no results. We learn from our colleagues in Burundi that there are still problems in the implementation of PBF with large delays in the payment of the subsidies, the essential drugs distribution system that still has monopolistic characteristics and the health facilities are less autonomous than desired.

PBF initiation of course participants

PBF initiation of course participants

Problems in Lesotho concern the slow roll out of the project while the Uganda PBF program is still reviewing how the successful Jinja pilot can be scaled up. EGPAF Mozambique is doing well in Xai-Xai and Nampula provinces but they may need to improve its design so that it will create ownership and buy-in also from the government.

The representatives from the Local Government in Uganda and the Civil Service Reform Commission in Malawi propose to initiative new multi-sector PBF programs.